


Our research
Why HIV persists.
How we move forward.
Explore the questions, discoveries, and clinical findings shaping REACH’s work toward a cure.
Go directly to A5386 ↗Explore our research
Four questions driving us forward.
HIV can survive treatment in a small pool of infected cells called the reservoir. These connected areas help us understand and overcome it.
Understand the reservoir
What allows HIV to persist in rare cells despite effective treatment?
Explore this research 02Help the immune system control HIV
How can immune cells and antibodies help contain HIV without daily medication?
Explore this research 03Help the immune system find infected cells
Why do some infected cells survive an immune attack?
Explore this research 04Understand how HIV stays silent
How does HIV’s place in a cell’s DNA shape its activity?
Explore this researchResearch area 01
Understand the reservoir
Antiretroviral therapy controls HIV, but a small population of infected cells can remain. We study which cells persist, how they change over time, and how the immune system responds.
All research areas ↑What makes this difficult?
HIV DNA can remain inside a cell even when no virus is detectable in the blood. Some copies are damaged. Others remain genetically intact and may contribute to HIV returning. Telling these apart is essential to interpreting a cure study.
Authentic reservoir clones, or ARCs, give researchers a rare opportunity to study cells derived from people living with HIV and examine why they survive. They connect observations in participants with questions that can be explored in the laboratory.
nature
Research article · February 24, 2026
Dynamic antigen expression and cytotoxic T cell resistance in HIV reservoir clones
Ferreira, Herrera and colleagues
Jones & Nussenzweig laboratories
A closer look at persistence
The reservoir,
within reach.
HIV can persist in rare infected cells despite effective treatment. Authentic reservoir clones, or ARCs, are models derived from human cells donated by people living with HIV. They let REACH scientists study the reservoir in a system grounded in human biology.
Work from the Jones and Nussenzweig laboratories examines where HIV sits within a cell’s DNA, why it becomes silent, and how infected cells escape immune attack—helping explain why HIV is so difficult to clear.
Research area 02
Help the immune system control HIV
Some people keep HIV at low levels for a period without daily medication. These individuals, often called controllers, offer clues to the immune responses that future treatments might strengthen.
All research areas ↑What are we trying to learn?
Clinical studies ask whether antibodies and other immune interventions can help the body contain HIV. REACH connects these outcomes with studies of the reservoir and of immune cells, including CD8 T cells that can recognize infected cells.
A5386 brings these questions together. Its reservoir findings and participants with extended time off ART give us new evidence to learn from. The goal is to understand why responses differ and how to make the benefit stronger and longer lasting.
From discovery to the clinic
A smaller reservoir.
New clues to HIV control.
The people behind the findings


A5386 broke new ground.
Now we build on it.
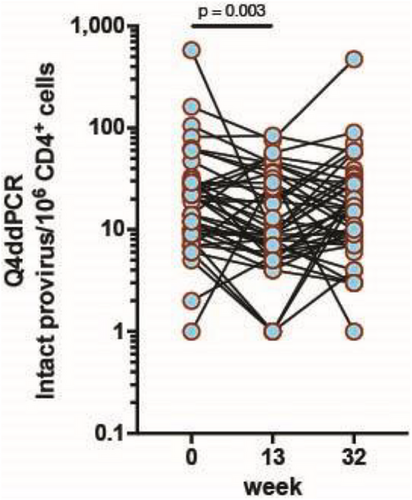
HIV’s reservoir is one of the toughest barriers to a cure. A5386 delivered a measurable reduction in genetically intact HIV—an exciting biological advance, alongside new clues to control without daily treatment.
Researchers also followed participants during closely monitored pauses in antiretroviral therapy (ART)—the medicines that suppress HIV. Together, these findings give REACH a strong foundation for building more durable control.
reduction in the intact HIV reservoir after five doses of N-803, an immune-stimulating treatment
participants remained off standard HIV medication for at least 24 weeks in updated REACH follow-up
Early clinical findings. Reservoir reduction was measured during treatment. Time off ART and study-defined viral control are different outcomes.
Explore the AIDS 2026 findings ↗Remodeling toward stem-like T cells associated with control
Itzy Miller’s analysis found that N-803, with or without broadly neutralizing antibodies, was associated with remodeling toward more stem-like, less exhausted CD8 T cells. This included increases in TCF-1-positive and stem-cell memory populations—features that support immune renewal and sustained responses.
The public conference findings linked this immune profile to HIV control after the study interventions, providing clues to the immune features that may support durable control. The role of treatment-associated remodeling in producing control remains under study.
 Enlarge figure
Scheck et al. · AIDS 2026, OAA1502, Figure 1 · JIAS. Reproduced unchanged under CC BY 4.0.
A novel combination. A meaningful advance.
The intact reservoir contains genetically complete HIV that remains inside infected cells despite treatment. A5386 measured a roughly 37% reduction after five doses of N-803—a concrete biological result to build on.
Researchers are still evaluating latency reversal—whether previously silent HIV becomes active. Additional results are needed before drawing conclusions. The study also observed changes in immune cells. Rachel Scheck presented the reservoir findings in an oral session at AIDS 2026.
What can we learn from HIV control without daily treatment?
A controller is someone who keeps HIV at low levels for a period without antiretroviral therapy. These participants offer some of the most exciting clues in HIV cure research.
In A5386, updated REACH follow-up as of September 10, 2026 identifies six participants who remained off ART for at least 24 weeks. The time-off-ART milestone does not by itself establish the same level of viral control in all six. Itzy’s analysis examines CD8 T cells—immune cells that can recognize and kill infected cells—and identifies cell features associated with control after the study interventions. Itzy also presented at an ACTG plenary session and shared the immune findings in an AIDS 2026 poster.
What sets the controllers apart? Which immune features matter most? Learning from these participants can help shape future studies aimed at stronger, longer-lasting control.
Our next chapter: learn, connect, build
REACH’s next phase will bring together the reservoir and immune findings to understand why responses differ. A5386 has moved the science forward. Now we will learn from the participants, connect the biological findings, and use that knowledge to shape the next generation of studies.
Study context & earlier findings
A5386 is a phase 1 study—an early stage of clinical research. The reservoir reduction above was measured during treatment. Earlier conference follow-up found measurements closer to their starting levels after dosing ended. A next goal is to extend the benefit and understand the participants who spent longer off HIV medication.
The six-participant figure reflects updated follow-up reported by the REACH team on September 10, 2026. ACTG’s July 2026 report described four participants at that earlier time point. Remaining off ART and meeting a study’s specific virus-control threshold are distinct outcomes.
Read the CROI 2026 poster ↗Related studies presented in 2025 and 2026

Marina Caskey presented a separate Rockefeller-led trial combining antibodies with an immune-modulating treatment at IAS 2025, and discussed combined immunotherapy at Keystone 2026. These studies help frame new questions about lasting HIV control.
IAS abstract book ↗Tools for the next questions
Better ways to study antibodies
Laboratory tools and computational analysis help researchers investigate antibody responses. This work complements the clinical studies.

University of Pittsburgh
Better antibody tools
Combining computer-based design with laboratory testing to develop antibody-based research tools.
Explore the study ↗Research area 03
Help the immune system find infected cells
Recognition is only part of the challenge. Some infected cells survive an immune attack. We study the barriers that prevent those cells from being cleared.
All research areas ↑Why can infected cells survive?
A cure strategy needs to account for both the immune response and the cells it encounters. REACH studies how infected cells become visible to the immune system, why some resist clearance, and what those differences mean for treatment.
Studies of human cells and laboratory models help distinguish promising biological findings from questions that still need to be tested in people.

Clayton laboratory
Why infected cells survive
Studying why HIV-infected immune cells called macrophages can survive attacks from natural killer cells, another part of the immune system.
Explore the study ↗
Jones laboratory
The barriers to clearance
Studying why some HIV-infected cells escape immune attack and survive, using laboratory and mouse studies.
Explore the study ↗These are laboratory and preclinical studies. They help explain persistence and guide future research.
Research area 04
Understand how HIV stays silent
HIV inserts a copy of its genetic material into a cell’s DNA. That copy can remain largely inactive, a state called latency. We ask how its location and the surrounding cell biology shape that silence.
All research areas ↑Why does location matter?
The reservoir contains cells with different histories and different patterns of HIV activity. Understanding those differences can help explain why HIV remains so difficult to eliminate during treatment.
REACH investigators study the relationship between HIV’s location in DNA, viral activity, and the persistence of infected cells. Findings from this work connect directly with the questions about reservoir measurement and immune clearance.
Related study · Journal of Experimental Medicine, 2024 ↗
Bieniasz & Mücksch
Why HIV falls silent
Exploring how HIV’s location within a cell’s DNA influences whether the virus stays silent or becomes active.
Explore the study ↗